
The 12th NVBP continues to expand and evolve with refined rules, disciplined competition, and new strategic options for pharma companies.
The 12th batch of China’s National Volume-Based Procurement (NVBP) was carried out in August 2026 as planned, with a record number of 65 drugs included in this round.
The latest tendering rules retain key elements of previous rounds while introducing several notable changes. Some longlisted candidates received exemptions for different reasons; the bidding and revival mechanisms were fine-tuned to limit over competition; and new pathways emerged for originators so it is no longer an all-or-nothing game. These changes were well received by the pharma industry in general, and many originators have been taking advantage of this to explore distinct strategies with different tradeoffs.
Refined rules
Similar to last round, the 12th NVBP built in a pre-screening process before finalizing the tender products, and 12 drugs from the longlist were exempted from the tender.
12 drugs were exempted from the 12th NVBP for different considerations
Exemption criteria in the 12th NVBP
| Exemption criteria | Drugs | Formulation | |
|---|---|---|---|
| Competitive landscape criteria not met | 1 | Lidocaine and Prilocaine | Ointment |
| 2 | Fluticasone Propionate | Inhalation | |
| 3 | Compound electrolytes | Injection | |
| 4 | Adenosine | Injection | |
| Subject to patent disputes | 5 | Ibrutinib IR | Capsule |
| 6 | Crisaborole | Ointment | |
| Critical medicines for assisted reproduction | 7 | Ganirelix | Injection |
| 8 | Cetrorelix | Injection | |
| 9 | Triptorelin | Injection | |
| National shortage medicines and clinically essential medicines vulnerable to shortages | 10 | Methotrexate | Injection |
| 11 | Cytarabine | Injection | |
| 12 | Nitroglycerin | Injection | |
- Four drugs were exempted from the 12th NVBP for competitive landscape considerations. Aspen's EMLA, the established lidocaine/prilocaine brand sold in China, was among those managed to stay out for now, as the number of generics meeting GQCE requirements fell short of the minimum of six players.
- Two drugs were exempted due to patent disputes. Crisaborole, for example, has a compound patent that expired in 2026, but its utility patent does not expire until February 2027, which helps it to stay out of the fray.
- Three drugs were exempted as they are considered critical medicines for assisted reproduction, including ganirelix, cetrorelix, and triptorelin. Another three drugs were exempted due to supply shortage concerns, including nitroglycerin, cytarabine, and methotrexate.
For the 65 drugs going into the tender, the bidding mechanism has been refined with two price anchors introduced for the first time, each incorporating standard deviation considerations. This creates a finite price range that is more reflective of where the bids cluster, while limiting the influence of extremely low bids. In addition, the revival mechanism and volume allocation rules have also been refined, so the high-priced bidders would have different ways to re-enter the game through Rules 2 and 3.
The 12th NVBP introduces dual price anchors to discourage irrational bids, and revival mechanisms for high priced bidders
Bidding rules
| Rule 1: Bidding price in comparable unit | |
|---|---|
| 1.1 | Bidding price <1.8x of the Price anchor 1
|
| 1.2 | Oral formulation: bidding price ≤0.1 RMB Small-volume injection: bidding price ≤1 RMB Large-volume injection: bidding price ≤2 RMB |
| 1.3 | Bidding price < Price anchor 2
|
| Rule 2: Revival mechanism (复活机制) – shortlisted | |
| 2.1 | Shortlisted bids follow the “1.8x” rule (入围复活)
|
| Rule 3: Revival mechanism (复活机制) – non-shortlisted (未入围) | |
| 3.1 | A non-shortlisted bidder may achieve selected status if :
|
| 3.2 | A non-shortlisted NMPA-designated reference product may be deemed selected with zero volume if it accepts a price:
|
| 3.3 | Other compound amino-acid subtypes: deemed selected with zero volume If compound amino acid 18AA-VII is selected, eligible adult amino-acid subtypes may be deemed selected by accepting:
|
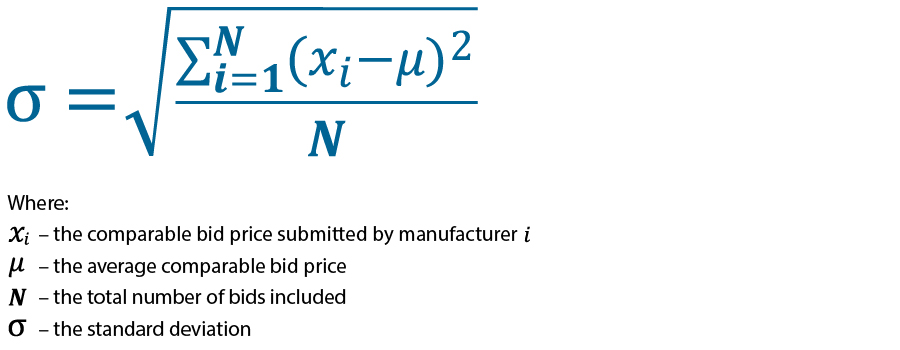
- Price Anchor 1 provides a baseline for regular bids. It is defined as the higher of (i) the lowest comparable bid or (ii) the average comparable bid minus one standard deviation. This prevents an exceptionally low bid from automatically pulling the benchmark down.
- Price Anchor 2 introduces a lower limit for regular bids, and is calculated as the average comparable bid minus two standard deviations. A bid below this threshold can still qualify as a winner, but receives zero committed procurement volume. This reduces the incentive to submit an extremely low bid.
- The revival mechanism is now extended to include both shortlisted and non-shortlisted bidders. In particular, Rule 2 provides revival opportunities for shortlisted candidates, and Rule 3 provides revival pathways for originators to win without committed volume, allowing them to preserve selected status and hospital listing without having to compete aggressively in the initial round of price-based bidding.
- Volume allocation rules have also been updated with intricate formulae, with the purpose to limit over concentration towards low-price bidders and better reflect clinical preferences.
The 12th NVBP links committed volume to supplier count, product characteristics and bidding pathways
Volume allocation rules
Stage 1: Brand-based allocation
Initial committed volume
=Brand-level reported volume×(Ratio 1−Ratio 2)×Ratio 3
| # of winners | Ratio 1 | Product | Ratio 2 |
|---|---|---|---|
| 1 | 50% | Other products | 0% |
| 2 | 60% | 4 designated products | 10% |
| 3 | 70% | 17 designated products | 20% |
| ≥4 | 80% |
| For supplier selected under Rule 1 or Rule 2 | Ratio 3 |
|---|---|
| ▪ Normally | 100% |
| ▪ Bid price < Price anchor 2 | 0% |
| For high-demand non-shortlisted suppliers selected under Rule 3.1: | Ratio 3 |
| ▪ Bid price ≤ Price anchor 1 | 80% |
| ▪ Price anchor 1 < bid price ≤ 1.4× Price anchor 1 | 50% |
| ▪ 1.4×Price anchor 1 < bid price ≤ 1.8× Price anchor 1 | 30% |
Stage 2: Institution-led allocation of remaining volume
After Stage 1, the remaining volume is broadly: National reported demand×(Ratio 1−Ratio 2)−∑Stage 1 volumes
Healthcare institutions then choose how to allocate this remaining volume among the product’s volume-bearing selected suppliers.

Disciplined competition
Competition remains intense in the 12th NVBP, as many products have over 20 bidders in the game.
Top 10 competitive products in 12th NVBP1
| Product | # of manufacturers passing GQCE | MNC originator |
|---|---|---|
| Vonoprazan fumarate tablets | 58 | Takeda |
| Vitamin B6 injection | 54 | |
| Sacubitril valsartan tablets | 34 | Novartis |
| Nicardipine injection | 34 | LTL Pharma |
| Bisoprolol fumarate and amlodipine besilate tablets | 33 | Merck |
| Bumetanide injection | 30 | |
| Compound potassium hydrogen phosphate injection | 29 | |
| Isavuconazole Injection | 25 | Pfizer |
| Azilsartan medoxomil tablets | 24 | Takeda |
| Calcium chloride injection | 23 | |
| ... | ... | |
Originator winner Originator opting out | ||
On the flip side, the revised rules have played an important role in discouraging irrational bidding and over competition purely based on price.
- Previous NVBP rules could incentivize manufacturers to bid aggressively on price in order to secure disproportionate volume. The dual-anchor mechanism introduced in the 12th batch is explicitly designed to discourage that, as the bids below Price Anchor 2 will receive no volume guarantee.
- The bidding rules further require companies with bids below Price Anchor 2 to submit a formal declaration to justify their pricing, including a cost breakdown to demonstrate that the bid is not below the company’s cost position.
New pathways
One of the most notable implications of the new framework is the emergence of new options for originators. As a result, the 12th NVBP saw a record number of originators qualified as tender winners.
Originator as NVBP winners
Historically, participation in NVBP could present originators with a dilemma with a binary outcome: either make a substantial price concession to compete for volume, or opt out and risk losing hospital access. The 12th NVBP introduces a meaningful middle ground through the revival mechanisms, as an eligible non-shortlisted originator can be deemed selected if it accepts a price within the specified threshold, while receiving zero committed procurement volume.
As a result, nine originator products made it through the revival mechanism, while another originator Ultravist secured a winning bid through regular tender.
- Entresto obtained zero-volume selected status in chronic heart failure, enabling it to maintain market access without competing directly for guaranteed volume. Its primary indication, hypertension, remains protected by patent rights extending to 2031, allowing the originator to pursue different commercial strategies across the two indications.
- Ultravist illustrates a different strategy. As a hospital-centric contrast agent with high substitution risk, maintaining routine hospital procurement is strategically important with limited alternatives. Ultravist therefore took part in the regular bidding and received volume commitment in return.
In fact, originators may now choose from four pathways under the new rules, each with distinct trade-offs across price, volume, and access.
Under the latest 12th NVBP, originators have different options with distinct trade-offs
NVBP scenarios for originator
| A Regular winner | B Revival winner with volume | C Revival winner with no committed volume | D Opting out of NVBP | |
|---|---|---|---|---|
| Price | Significant price discount required to win for originator | No higher than 1.8x Price anchor 1, and below the maximum valid bid price | Moderate price discount required to win without committed volume | Slight price cut of ~20% required as losing bidder |
| Volume | ≤50% of total reported volume for the drug Opportunity for NVBP-out volume and non-NVBP vol. | Part of reported volume for the brand + eligible for hospital volume, NVBP-out volume and non-NVBP vol. | Eligible for NVBP-out volume (~20% of reported volume if ≥4 winners) and non-NVBP volume | May not be preferred in public hospital Can strive for NVBP-out volume and non-NVBP vol. |
| Access | Broad access across existing hospitals Opportunity exists to expand hospital coverage as winner | Broad access across existing hospitals Opportunity exists to expand hospital coverage as winner | Hospital listing can retain across existing hospitals | Delisting from public hospital likely as a losing bidder |
| Additional consideration | May be considered for hospital only products with portfolio synergy, e.g. lopromide | May be considered for products for which first prescription in hospital would be important | May be considered for products suitable for alternative channel coverage, e.g. e-channel, private hospitals etc. | |
- As a regular bidding winner under Rule 1, like Ultravist. Companies will bid on price to secure committed procurement volume in return. The regular winner status can also help maintain and potentially expand hospital access by competing for non-NVBP volume.
- As a revival winner with committed volume under Rule 2. Eligible shortlisted originators can regain winner status by accepting a price below the highest valid bidding price for that drug, while committed volume is allocated based on the final bid price on a sliding scale, creating more flexibility to balance price and volume.
- As a revival winner with no committed volume under Rule 3, like Entresto. Eligible originators can obtain winner status at a more moderate price concession after dust settles, without receiving committed procurement volume. While the committed volume is zero, the revived winner status helps preserve hospital listing, with the possibility to capture non-NVBP volume. This pathway can be relevant for originators striving to preserve hospital presence and initial prescriptions with limited price concession.
- Opting out of NVBP. Companies that remain outside NVBP retain greater pricing flexibility, at the risk of major disadvantages in market access and hospital listing.
Strategic implications
With the refined rules and new pathways, the 12th NVBP aims to bring back some balance to the once heated price-based competition. Pharma players would benefit from proactively adapting to the changes and adjusting priorities at each step of the NVBP journey.
- Pre-NVBP: assess the latest tendering and exemption rules and implications, map out key stakeholders and competitive scenarios, and have in place a gameplan well ahead of the tender.
- During NVBP: navigate the different pathways for the optimal tradeoffs. Under the latest rules, a player may become a regular winner with committed volume, or a revived winner with or without committed volume, or opt out altogether, each with materially different implications on price, volume, and access.
- Post-NVBP: reconfigure go-to-market model to embrace the changes to the underlying market and access environment. For the originators without committed volume, they would need to shift their priorities towards preserving established hospital access and defending the existing business, while actively pursuing non-NVBP volume. For those opting out, proactive migration to alternative channels can be even more mission critical, and requires early planning and systematic retooling of the commercial model elements.
Given the dynamic changes in China pharmaceutical market, it is safe to predict that the latest round of NVBP is not the end, it is not even the beginning of the end. Future success will increasingly depend on agility to stay ahead of the game, and tenacity to stay in the game.
Get in touch to discuss the NVBP updates in more detail.